Postpartum NFP: Charting With the Billings Method

What to notice as your cycle begins to return.
After birth, your cycle may feel unfamiliar for a while.
There is postpartum bleeding. Healing. Feeding around the clock. Sleep that comes in pieces. And somewhere in the middle of all of that, fertility will eventually begin to return.
For some women, that happens relatively soon. For others, especially while breastfeeding, it may take months.
The Billings Ovulation Method, a form of natural family planning, does not ask you to predict when your old cycle will come back. Instead, it gives you a way to learn the pattern you have now, recognize when that pattern changes, and record what you actually observe.
Postpartum charting is less about counting days and more about paying attention.
A note before we begin: Corvia is a cycle-charting and education tool, not medical care. A Billings chart records sensation at the vulva, visible discharge and bleeding. It cannot measure hormone levels, diagnose a postpartum condition or tell you exactly what is happening inside the ovaries.
The First Weeks Are Their Own Season
The early weeks after birth are primarily about recovery.
Your uterus is healing, hormones are shifting, and postpartum bleeding and discharge, called lochia, may continue for several weeks. ACOG describes lochia as a normal part of healing after birth and notes that bleeding should generally become lighter over time. (ACOG)
For many women, ovulation has not yet returned during these earliest weeks. But there is no date on the calendar when fertility is guaranteed to switch back on.
Research in non-breastfeeding women found that most did not ovulate before six weeks postpartum, although a small number did. Across the studies, the average timing of first ovulation varied considerably. (PubMed)
So postpartum charting does not begin with:
I'm only four weeks postpartum, so I know I'm infertile.
or:
My period hasn't returned, so fertility hasn't either.
It begins with observation.
You Can Begin Observing Before Your Period Returns
Official WOOMB guidance recommends beginning Billings observations around three weeks after birth, or as lochia diminishes enough for you to distinguish the daily sensation at the vulva. (Woomb International)
That does not mean you need to understand your chart immediately.
At first, you are simply rebuilding the habit of noticing what the vulva felt like as you moved through the day, whether you saw any discharge, and whether there was bleeding or spotting.
Beginning observations is also different from being medically cleared to resume intercourse or other postpartum activity. Your own postpartum care guidance still applies.
Your First Period Is Not the Starting Line
One of the most useful things to understand postpartum is that ovulation can happen before the first menstrual period.
It does not always happen that way. In the systematic review of non-breastfeeding women, only a portion of first postpartum periods were preceded by ovulation. But because ovulation can occur first, waiting for menstruation is not a reliable way to know that fertility has returned. (PubMed)
Billings approaches the question differently.
Instead of waiting for a period or predicting an ovulation date, you begin with the pattern you are actually observing.
Postpartum Billings Starts With the BIP
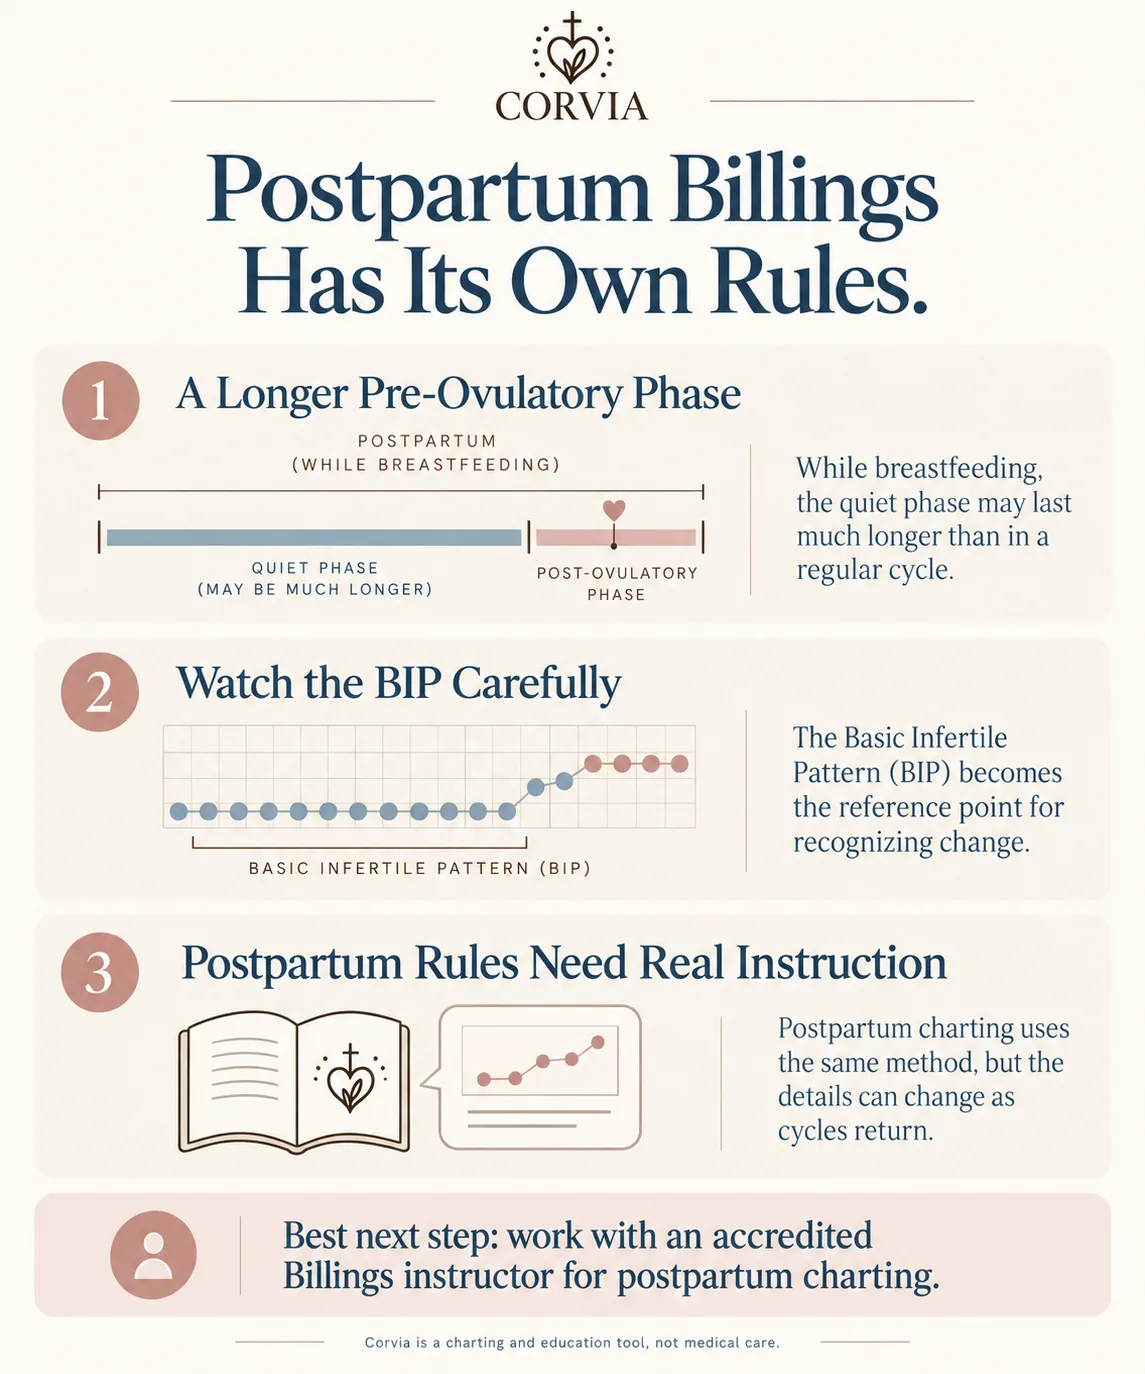
During a familiar monthly cycle, the pre-ovulatory part of the chart may last only several days.
Postpartum, it can last weeks or months.
That makes the Basic Infertile Pattern, or BIP, especially important.
Within the Billings Method, a BIP is an established unchanging pattern during the pre-ovulatory infertile phase. Some women may have a dry BIP. Others may establish an unchanging discharge pattern or, during a prolonged pre-ovulatory phase, a combination pattern. WOOMB has specific rules for determining when those patterns are established. (Woomb International)
The important word is established.
A few similar days do not automatically become your BIP.
This is one of the places where an accredited Billings instructor can be particularly helpful. If you are using the method to make pregnancy-related decisions postpartum, the instructor can help you apply the actual Billings rules to the pattern you are seeing rather than trying to establish a BIP from a simplified blog explanation.
A Quiet Chart Is Still a Chart
There may be a lot of sameness postpartum.
Day after day may look nearly identical.
If you are accustomed to watching a recognizable monthly pattern unfold, weeks of the same observation can feel as though nothing is happening.
But within Billings, an established BIP gives you a reference point.
You are not waiting for Cycle Day 14.
You are not asking when an app thinks ovulation should happen.
You are asking something simpler:
Is today the same as my established pattern, or has something changed?
That question matters even when the pre-ovulatory phase is very long.
When the Pattern Changes
Eventually, you may notice something different.
Perhaps your established pattern has been dry and you begin noticing dampness or discharge. Maybe you have had the same unchanging discharge for weeks and the sensation suddenly feels different. You might notice spotting or bleeding.
Within Billings, a change from an established BIP is treated as potential fertility, and the method has specific Early Day Rules for how those changes are handled. WOOMB specifically includes changes in sensation, visible discharge, bleeding and spotting. (Woomb International)
Sometimes the change continues.
Sometimes the familiar BIP returns.
And sometimes this happens more than once before a Peak is eventually recognized.
What the chart tells you is straightforward:
something in the observation changed.
It does not necessarily tell you why.
You Don't Need to Decode the Ovary
Postpartum fertility is sometimes described as the ovaries "waking up," having "false starts," or repeatedly "trying to ovulate."
Those phrases can be useful shorthand, but they make the chart sound more precise than it actually is.
If a different observation appears and then your established BIP returns, you know exactly that: the pattern changed and then returned.
You cannot determine from the Billings chart alone whether a particular follicle was developing, whether estrogen reached a certain value, whether that follicle regressed, or whether an ovary "tried" to ovulate.
And you do not need to.
Billings asks you to record what you actually notice rather than inventing a hormonal explanation for every day on the chart.
Peak Still Means the Same Thing
Postpartum does not change the Billings definition of Peak.
Peak is the last day of slippery sensation at the vulva.
It is recognized retrospectively, once the following day is no longer slippery. The following day does not necessarily have to be completely dry. (Billings LIFE)
Official Billings teaching places Peak very close to the time of ovulation. But it is still an observed fertility sign rather than direct medical confirmation that an egg was released. (Billings LIFE)
That distinction is worth keeping clear:
You can recognize a Billings Peak without claiming that your chart directly measured ovulation.
Breastfeeding Can Stretch the Timeline
Breastfeeding can delay the return of ovulation, sometimes for quite a while.
How long that lasts varies enormously. WOOMB specifically notes that every mother-baby pair is different and that the timing of returning fertility cannot be predicted for an individual woman simply from breastfeeding behavior. (Woomb International)
Night feeds may change. Your baby may begin sleeping longer. Supplementation may be introduced. Eventually solids and weaning become part of the picture.
Those changes may affect the fertility landscape, but they are not a countdown clock.
Your observations are still the part you can actually chart.
Breastfeeding Is Not the Same Thing as Billings
You may also hear about the Lactational Amenorrhea Method, or LAM.
LAM is a separate family-planning method with specific criteria. Current CDC guidance requires all three: menstruation has not returned, the baby is younger than six months, and the baby is fully or nearly fully breastfed with feeding intervals generally no longer than four hours during the day or six hours overnight. (CDC)
Billings uses a different approach based on daily observations and its own postpartum rules.
For a deeper look at breastfeeding specifically, our separate guide covers that season in more detail:
Charting the Billings Method While Breastfeeding: The Full Guide
What About Corvia's 28-Day Learning Mode?
Corvia offers a 28-day learning mode for postpartum and other extended-cycle situations.
It gives you room to build the habit of observation without expecting your cycle to fit neatly into a monthly calendar.
But there is an important distinction:
The 28 days are a Corvia feature, not a Billings rule.
Finishing the 28 days does not automatically establish your Basic Infertile Pattern.
And learning mode does not mean fertility cannot change during those 28 days. If your observation changes, record what you actually notice.
The chart follows your body, not the other way around.
The First Returning Cycles May Look Different
When menstruation and ovulation begin returning, your cycles may not immediately look like the ones you remember from before pregnancy.
The pre-ovulatory phase may remain long. Cycle length may vary. Mucus patterns may seem less familiar, particularly if you are still breastfeeding.
There is no universal number of cycles by which everything should look "normal" again.
That is another reason postpartum is a poor time to compare every chart with a textbook 28-day cycle.
Your chart does not have to look textbook to be useful.
What Your Chart Can, and Cannot, Tell You
A postpartum Billings chart can become a surprisingly useful record.
It can preserve your bleeding pattern, your established BIP, changes from that pattern, visible discharge, changes in sensation, slippery sensation, a recognized Peak and how those observations developed over time.
That can be helpful when reviewing the chart yourself, working with an instructor or describing the pattern to a healthcare professional.
But the chart cannot directly measure estrogen, progesterone or prolactin. It cannot show you a developing follicle. It cannot determine why you are bleeding or diagnose a postpartum complication.
That boundary does not make the chart less meaningful.
It simply keeps the information honest.
The chart tells you what you observed.
When an Instructor Can Help
Postpartum is one of those seasons when Billings can become more nuanced.
You may find an accredited instructor especially helpful if you are unsure whether you have correctly established your BIP, your established pattern changes, you are seeing repeated changes and do not understand how the Billings rules apply, or you are using the method to make pregnancy-related decisions during the postpartum transition.
An instructor helps with the Billings pattern and rules.
Medical questions belong with your healthcare professional.
Those are different roles, and one does not replace the other.
When the Chart Is Not Enough
Postpartum bleeding and discharge are expected while your body heals. But the chart cannot determine whether a particular symptom is normal or has a medical cause.
ACOG advises contacting a healthcare professional for postpartum warning signs such as unusually heavy or gushing bleeding, large clots, feeling faint or dizzy, fever and chills, abdominal pain or tenderness, or foul-smelling discharge. ACOG describes soaking through two pads an hour for more than one to two hours as a sign of postpartum hemorrhage requiring prompt attention. (ACOG)
If something is medically concerning, your chart can help document what happened.
It should not be asked to diagnose it.

What Do We Know About Billings Effectiveness Postpartum?
Billings has specific official rules for lactation, prolonged pre-ovulatory phases and the return of fertility. (Woomb International)
The evidence specifically measuring pregnancy-prevention effectiveness during the postpartum period, however, is limited.
A 2022 systematic review found only four eligible studies of specific fertility-awareness methods among postpartum women. None was rated high quality; the authors concluded that the evidence for individual methods during this season remains very limited and mostly low quality. Billings was one of the methods represented in the available research. (PubMed)
That does not mean Billings cannot be used postpartum.
It means we should not turn limited research into a stronger effectiveness promise than the evidence supports.
If pregnancy avoidance is particularly important in this season, learning the complete postpartum Billings rules with an accredited instructor gives you more than a short article ever could.
Learn the Pattern You Have Now
It is tempting after birth to wait for your "real cycle" to come back.
But postpartum is already part of your reproductive story.
The long quiet stretch counts.
The first change counts.
The strange-looking chart counts.
And eventually, the first recognized Peak becomes part of that story too.
You do not need to predict when fertility will return or explain every observation in terms of hormones and ovaries.
Start somewhere simpler.
Notice what is there today.
Record it honestly.
Learn the pattern you have now.
And let understanding build from there.
Want to understand Billings before you begin charting?
Billings 101 walks through the method in 19 short lessons, completely free.
Learn the Billings Method →Frequently asked questions
When should I start charting after birth?
Official WOOMB postpartum guidance recommends beginning Billings observations around three weeks after birth or as lochia diminishes enough that you can distinguish your daily vulvar observation. (Woomb International)
Beginning observations is separate from being medically cleared to resume intercourse or other postpartum activity.
Can fertility return before my first postpartum period?
Yes. Ovulation can occur before the first postpartum period, although it does not necessarily do so in every woman. Research in non-breastfeeding women shows considerable variation in the timing of both first ovulation and first menstruation after birth. (PubMed)
That is why Billings does not wait for menstruation to begin observing fertility signs.
Can I use Billings while breastfeeding?
Billings has specific guidance for lactation, prolonged postpartum amenorrhea and returning fertility. (Woomb International)
Because postpartum patterns can be more complicated, and research on pregnancy-prevention effectiveness in this particular population is limited, working with an accredited instructor is especially useful when you are relying on the method for pregnancy-related decisions. (PubMed)
What if my postpartum observations keep changing?
Record what you actually notice.
During a prolonged pre-ovulatory phase, a change from an established BIP may appear and the BIP may later return. Billings has specific rules for handling those changes. (Woomb International)
An instructor can help with the Billings interpretation. Bleeding, pain, fever or other symptoms that concern you belong in a medical conversation rather than being explained from the chart alone.
Sources and further reading
- WOOMB International: Billings Ovulation Method and Managing Fertility During Lactation and Weaning. The primary Billings source used here for beginning postpartum charting, establishing the Basic Infertile Pattern, recognizing change and charting during lactation. WOOMB postpartum Billings guidance
- Billings LIFE: Key to Fertility Control: The Mucus / The Peak of Fertility. Official Billings material defining Peak and explaining its relationship to ovulation. Billings LIFE: Peak of Fertility
- Jackson E, Glasier A. Return of Ovulation and Menses in Postpartum Nonlactating Women: A Systematic Review. Obstetrics & Gynecology. 2011. Review of the timing of first postpartum ovulation and menstruation among non-lactating women. (PubMed)
- Redmond JJ, et al. Effectiveness of Fertility Awareness-Based Methods for Pregnancy Prevention During the Postpartum Period. Contraception. 2022. Systematic review of postpartum effectiveness evidence for fertility-awareness methods. (PubMed)
- CDC: Lactational Amenorrhea Method. Current criteria distinguishing LAM from breastfeeding generally and from fertility-awareness methods such as Billings. CDC: Lactational Amenorrhea Method
- American College of Obstetricians and Gynecologists: Postpartum Warning Signs. Guidance on postpartum bleeding, hemorrhage and infection symptoms that warrant medical attention. ACOG: Conditions to Watch for After Childbirth