The Billings Method During Perimenopause: What Changes and What Still Works

Perimenopause can make a cycle that once felt familiar suddenly seem unpredictable.
A period comes early. The next one comes late. Mucus appears, disappears and then returns. A Peak you used to recognize easily may become harder to identify. Some cycles may feel almost unchanged, while others look completely different.
That does not mean you have forgotten how to chart.
Your body is entering a new season.
The Billings Ovulation Method can still be used during perimenopause because it does not require your cycles to follow a calendar or repeat the same pattern every month. You continue doing what Billings has always asked you to do:
observe what is happening today.
Corvia can help you preserve that record as the pattern changes.
Corvia is a cycle-charting and education tool, not a medical diagnostic tool. Perimenopause can affect cycle length, bleeding and mucus patterns, but a chart cannot tell you why a change is happening or rule out another medical cause. New, heavy or concerning bleeding deserves a conversation with a qualified healthcare professional.
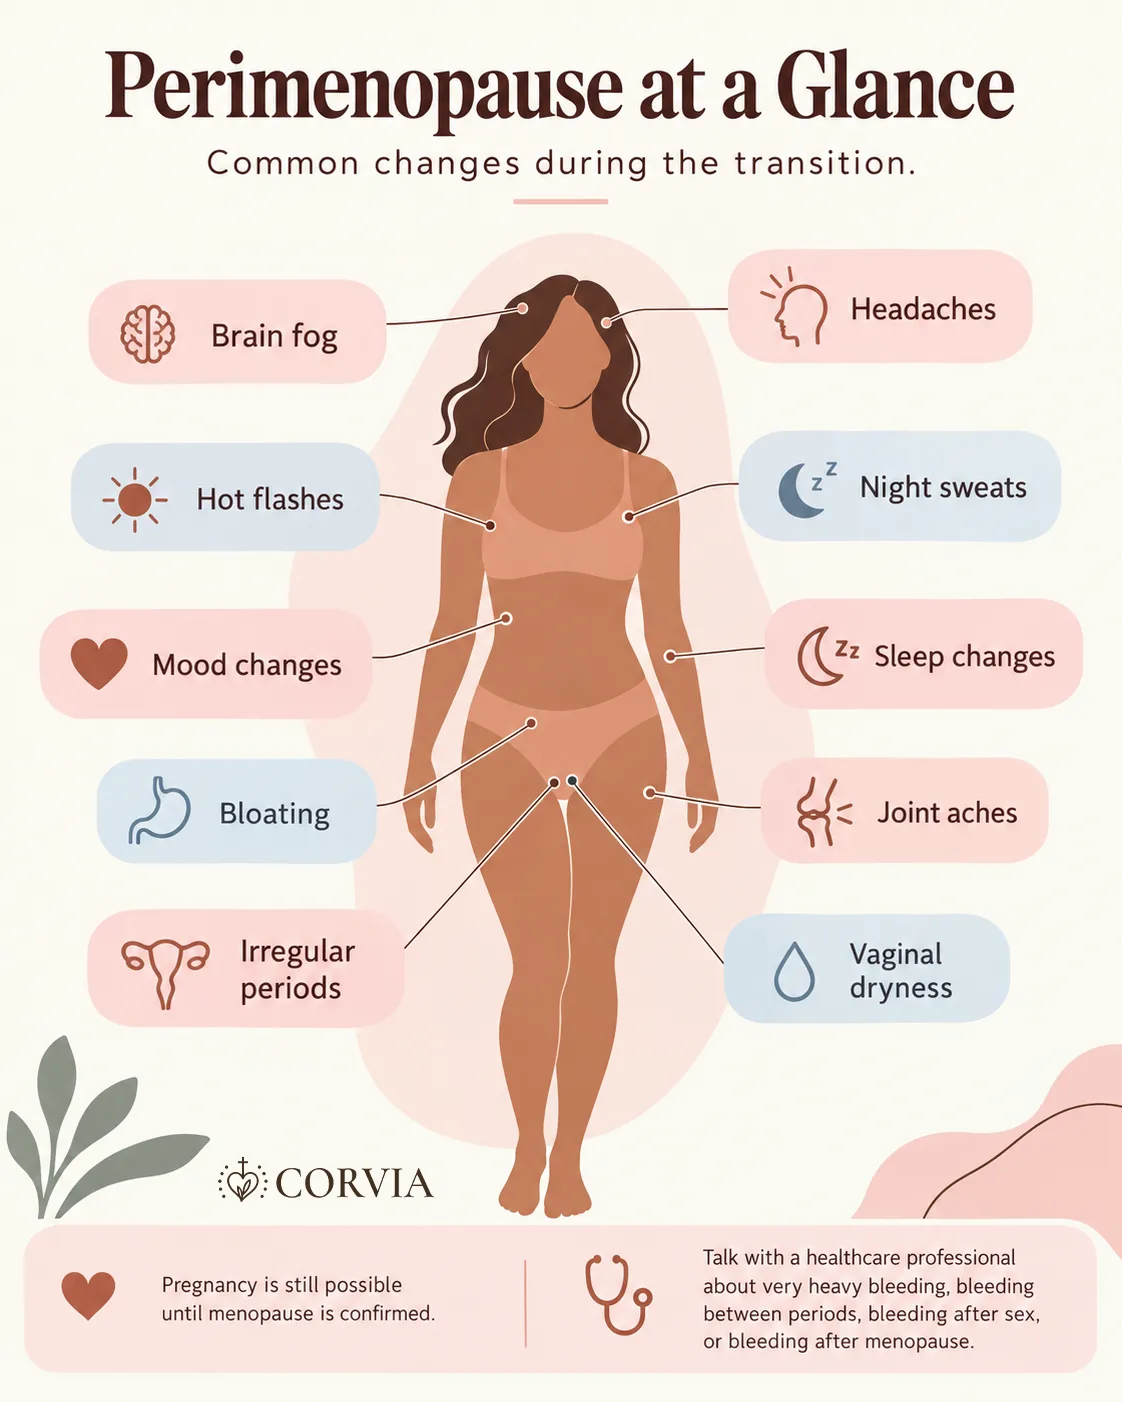
When the Pattern Starts to Change
Perimenopause is the transition leading up to menopause.
It often begins sometime in a woman's 40s, although it may start earlier or later. The transition can last several years, and every woman's experience is different.[1][2]
One of the earliest things many women notice is a change in the cycle itself.
Periods may come closer together for a time. Later, they may become farther apart. Some cycles may be much longer than they used to be. Others may be shorter.
Ovulation also becomes less consistent as the transition progresses.[2]
Hormones do not simply fall in a smooth, predictable line. Estrogen and progesterone patterns can become more variable from one cycle to another.[3]
That is why a cycle that once followed a familiar rhythm may begin doing something new.
Billings Does Not Need a Prediction
Perimenopause makes prediction less useful because the timing of ovulation and menstruation becomes less predictable.
Billings approaches the cycle differently.
You are not trying to guess:
When should I ovulate?
You are asking:
What am I observing today?
Official Billings teaching specifically addresses the years approaching menopause, when cycles may become shorter, longer or increasingly irregular.[4][5]
The method still centers on the same observations: sensation at the vulva, the appearance of any mucus or discharge, bleeding and the changing pattern across the cycle.
The chart does not need to resemble last month's chart in order to be useful.
Your Basic Infertile Pattern May Change
For many women, the Basic Infertile Pattern, or BIP, has been familiar for years.
That pattern may change during perimenopause.
You may experience long stretches of dryness. You may have an unchanging discharge pattern. Some women may develop a combination of the two.[4]
What matters is not assuming that your old pattern still applies simply because it used to.
A new or changing BIP needs to be identified according to the Billings guidelines.
If you are using Billings to avoid pregnancy, this is an especially useful time to work with an accredited Billings instructor rather than deciding on your own that a new pattern represents infertility.
Corvia can preserve the observations.
Instruction helps you interpret them correctly.
Mucus May Come and Go
One of the more confusing parts of perimenopause can be mucus that appears and then disappears.
You may be in an established Basic Infertile Pattern when something changes.
Perhaps the sensation changes.
Perhaps mucus appears.
The pattern may continue developing toward Peak.
Or it may return to the previous Basic Infertile Pattern without a recognized Peak.[4]
This can happen more than once during a long cycle.
The important thing is not to decide that every mucus patch tells you exactly what happened inside the ovary.
A change tells you that something changed.
The chart does not directly measure estrogen. It does not show individual follicles. It cannot prove that ovulation did or did not occur.
Billings records the outward pattern.
It does not diagnose the physiology underneath it.
Peak Still Means the Same Thing
Perimenopause does not change the Billings definition of Peak.
Peak is the last day of slippery sensation at the vulva.
You recognize it retrospectively when the following day is no longer slippery.[6]
The days after Peak do not have to become completely dry. That is an important distinction.
You may still recognize Peak clearly in some perimenopausal cycles. In other cycles, a clear Peak pattern may never develop.
The method does not ask you to force one onto the chart.
If you are uncertain whether a pattern meets the Billings definition of Peak, an accredited instructor can help you review it.
A Changing Chart Is Still Useful
Perimenopause is exactly the kind of season when a record becomes valuable.
You may begin noticing:
- cycles becoming longer or shorter
- more variation from one cycle to another
- mucus patterns appearing less often
- changing Basic Infertile Patterns
- cycles with a recognizable Peak
- cycles without one
- changes in bleeding
Those observations do not diagnose perimenopause.
But they can help you see that your cycle is changing over time.
That can also make it easier to describe the change to a healthcare professional.
Instead of saying:
My periods have been weird lately.
you may be able to say:
My cycles used to be around this length. Over the last six months, they have changed like this.
Or:
This bleeding happened between periods.
Or:
This is when the new pattern started.
The chart gives you the record.
Your healthcare professional evaluates what it may mean medically.
Pregnancy Is Still Possible
Perimenopause does not mean fertility disappears all at once.
Ovulation generally becomes less frequent as menopause approaches, but it can still occur unpredictably.[2]
That means pregnancy is still possible.
If you are using Billings to avoid pregnancy, careful application of the method remains important throughout this transition.
A long cycle is not automatically infertile.
A missed period is not automatically menopause.
And irregular ovulation is still ovulation when it occurs.
For this reason, couples using Billings to avoid pregnancy may benefit from closer contact with an accredited instructor as the woman's patterns change.
When Does Perimenopause Become Menopause?
Natural menopause is reached after 12 consecutive months without a menstrual period or spotting, when there is no other explanation for the absence of bleeding.[1]
Until that point, a woman is still in the menopausal transition.
That twelve-month mark matters because occasional ovulation can still occur during perimenopause.
Once natural menopause is confirmed, fertility charting is no longer needed for pregnancy avoidance.
You may still choose to record symptoms or other health information if the record is useful to you.

Some Bleeding Changes Deserve a Conversation
Cycle changes are common during perimenopause.
But not every new bleeding pattern should automatically be blamed on menopause.
Talk with a healthcare professional if you notice things such as:
- very heavy bleeding
- bleeding that lasts much longer than your usual period
- spotting or bleeding between periods
- bleeding after sex
- bleeding or spotting after you have already gone 12 months without a period
ACOG recommends evaluation of abnormal bleeding during this life stage because there are many possible causes, including fibroids, polyps and other conditions that may need treatment.[7]
Bleeding after menopause should always be evaluated.
Your chart may help you show when and how often the bleeding happened.
It cannot tell you the cause.

What Corvia Can Help You Keep
Perimenopause can make the cycle feel less orderly.
Corvia gives those changing observations somewhere to live.
You can keep a record of:
- bleeding
- daily Billings observations
- Peak when you recognize it
- changing cycle lengths
- changes from your usual pattern
- personal notes or symptoms you want to remember
Corvia does not decide whether a cycle was ovulatory.
It does not diagnose perimenopause.
It does not tell you why bleeding changed.
And it does not replace instruction in the Billings Method or medical care when you need it.
What it can do is help you preserve the story as it unfolds.
The Pattern Is Changing. You Can Keep Observing.
Perimenopause is a transition.
Not a failure.
Not your body forgetting how to work.
And not a season you need to force into the pattern you had ten years ago.
Your cycle may be changing because your reproductive life is changing.
Billings gives you a way to meet that change without demanding prediction.
Observe the day in front of you.
Record what you notice.
Let the pattern tell its own story over time.
This is not your body breaking. It is your body changing.
Want to understand Billings before you begin charting?
Billings 101 walks through the method in 19 short lessons, completely free.
Learn the Billings Method →Frequently asked questions
Can I still use the Billings Method if my cycles are very irregular?
Yes.
Billings does not require every cycle to be the same length. Official Billings guidance specifically addresses the years approaching menopause, when cycles may become shorter, longer or increasingly unpredictable.[4][5]
If you are using Billings to avoid pregnancy, changing patterns are a good reason to stay in contact with an accredited instructor.
Do I need a new Basic Infertile Pattern in perimenopause?
Possibly.
Your Basic Infertile Pattern may change as cycles become longer or your mucus pattern changes. Official Billings guidance describes dry, discharge and combined patterns during the perimenopausal years.[4]
Do not assume that a newly repeated pattern is infertile simply because you have seen it for several days.
If pregnancy avoidance matters, work with an accredited instructor to establish your current BIP correctly.
What if mucus appears and then disappears?
That can happen during perimenopause.
A change from your Basic Infertile Pattern is treated as potential fertility according to the Billings rules. Sometimes the pattern continues and Peak is eventually recognized. Other times it returns to the previous Basic Infertile Pattern without a recognized Peak.[4]
The chart alone cannot prove whether ovulation occurred.
It records the pattern you observed.
What exactly is Peak during perimenopause?
Peak means the same thing it does at any other reproductive stage: the last day of slippery sensation at the vulva.[6]
You know it was Peak when the following day is no longer slippery.
The post-Peak days do not have to be completely dry.
If you are uncertain whether a day meets the Billings definition of Peak, review the chart with an accredited instructor.
At what age does perimenopause usually begin?
Many women begin noticing the transition sometime in their 40s, although it can begin earlier or later.
Most women reach menopause between ages 45 and 55.[1]
Age is only one part of the picture. Changes in menstrual patterns and symptoms help healthcare professionals understand where a woman may be in the transition.
Can my Billings chart tell me that I am in perimenopause?
No.
Your chart may show changes that are common during perimenopause, such as increasingly irregular cycles, changing mucus patterns or fewer recognizable Peak patterns.
But similar changes can happen for other reasons.
Perimenopause is evaluated using your age, menstrual history, symptoms and medical evaluation when appropriate.
Your chart can be useful information to bring into that conversation, but it does not make the diagnosis.
Is pregnancy still possible during perimenopause?
Yes.
Ovulation becomes less frequent as menopause approaches, but it can still happen unpredictably.[2]
If avoiding pregnancy is important, continue using your fertility-awareness method until menopause has been confirmed according to appropriate guidance.
Should I keep charting after menopause?
You can if the record remains personally useful, but fertility charting is no longer necessary for pregnancy avoidance once natural menopause has been confirmed.
Any vaginal bleeding or spotting after menopause should be evaluated by a healthcare professional.[7]
Sources and further reading
- National Institute on Aging: What Is Menopause? Overview of perimenopause, the usual age range, symptoms and the definition of natural menopause. National Institute on Aging: What Is Menopause?
- The Menopause Society: Perimenopause Current patient guidance on changing cycles, less-frequent ovulation and pregnancy risk during the menopausal transition. The Menopause Society: Perimenopause
- Prior JC. The Ageing Female Reproductive Axis II: Ovulatory Changes With Perimenopause. Review of changing ovulation, estrogen and progesterone patterns during the menopausal transition. PubMed
- WOOMB International: Billings Ovulation Method in the Peri-Menopausal Years Detailed official Billings guidance on changing cycles, Basic Infertile Patterns and fertility observations during perimenopause. WOOMB: Billings in the Peri-Menopausal Years
- Billings LIFE: Approaching Menopause? Official Billings overview of using the method as cycles become increasingly irregular. Billings LIFE: Approaching Menopause?
- Billings LIFE: How the Billings Ovulation Method Works Official explanation of the Basic Infertile Pattern, changing pattern, Peak and post-ovulatory phase. Billings LIFE: How the Method Works
- American College of Obstetricians and Gynecologists: Perimenopausal Bleeding and Bleeding After Menopause Guidance on common bleeding changes and patterns that deserve medical evaluation. ACOG: Perimenopausal Bleeding
- Harlow SD, et al.: STRAW+10: Stages of Reproductive Aging Workshop Consensus framework describing the stages of reproductive aging and the early and late menopausal transition. PubMed: STRAW+10
- New content


